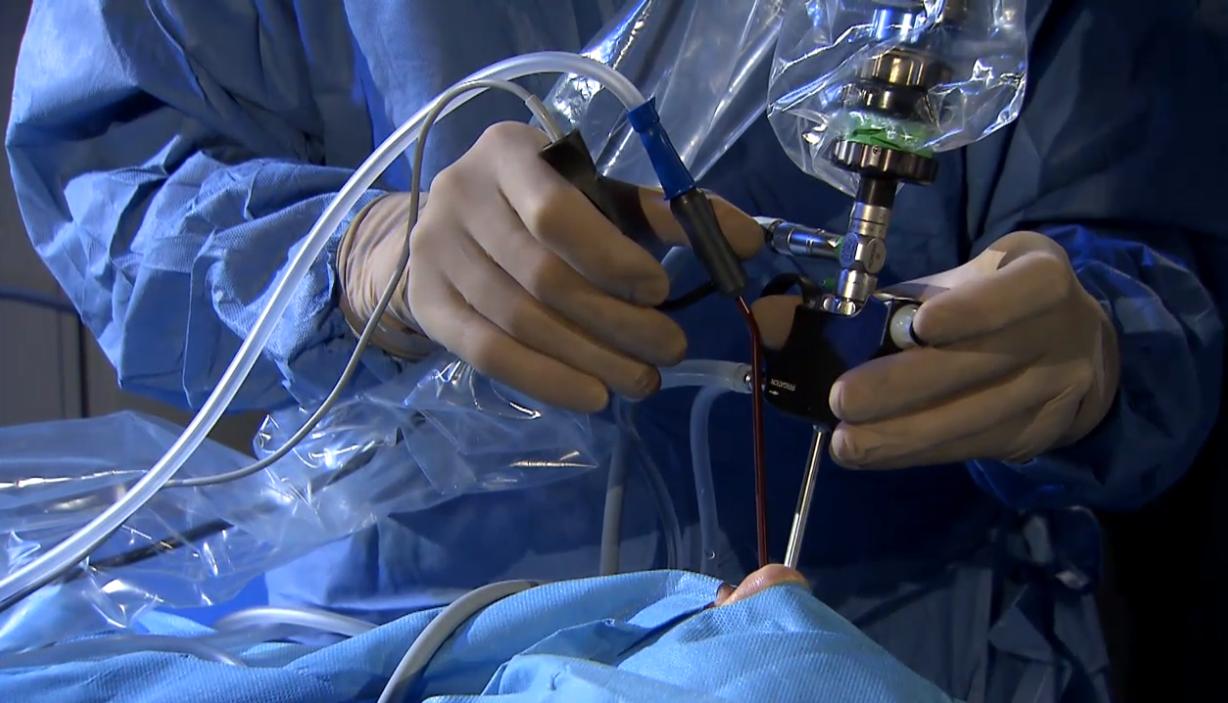
Modern endoscopes are specialized instruments connected via a lens-based optical system to a camera system and a light source. Through the smallest access routes, they provide excellent HD-quality images from deep-seated surgical regions or a cavity (e.g., the ventricular system or cysts)[^1]. At the same time, microinstruments can be introduced through endoscopic systems to perform surgical procedures through a minimally invasive approach under full visual control.
Historical background
The first endoscopic procedures on the brain were performed as early as the beginning of the 20th century. However, standardized use in routine clinical practice did not begin until the start of the 21st century. The main reasons for the delay were inadequate miniaturization of the endoscopes and light sources that were far too weak. At the end of the 1980s, major technical improvements and the introduction of endoscopic working instruments (laser, bipolar electrode, and mini forceps) led to a significant resurgence of this technique [^2]. Today, endoscopy is virtually indispensable in routine neurosurgical practice for certain procedures.
Terminology
Endoscope-guided microsurgery
In endoscope-guided microsurgery, an endoscope is used exclusively as the visualization instrument, while the surgical instruments are used alongside and parallel to it. The instruments resemble those used in microsurgery. Unlike the endoscope-assisted technique, no microscope is used. The advantage of the endoscope-guided technique compared with “through-channel” endoscopy is that bimanual dissection more closely resembles microsurgical dissection under the microscope[^10].
Endoscope-assisted microsurgery
In endoscope-assisted microsurgery (Endoscope-assisted microsurgery), the main part of the procedure is generally performed under microscopic visualization because of the better image resolution and three-dimensional view. Only some steps of the procedure are performed under endoscopic visualization. The endoscope is used mainly to visualize bony or dural corners and neurovascular structures[^10]
Applications
In neurosurgery, endoscopes are used, on the one hand, to support microsurgical operations, for example, to obtain a better view of areas that are difficult to visualize. On the other hand, certain procedures, particularly involving the Ventricular system, can be performed purely endoscopically, with various instruments available to the surgeon, such as an endoscopically usable laser, bipolar electrodes, or forceps. If necessary, endoscopes can be used in combination with a Neuronavigation system to provide additional orientation beyond visual control.
Overview of endoscopic procedures
Neuroendoscopic procedures are routinely used in the ventricular system and at the skull base. Intraventricular tumors and cysts are usually ideal lesions for an endoscopic procedure because the endoscopic approach causes only minimal damage to healthy brain parenchyma. In addition, the surgical field can usually be visualized well because the ventricular system is filled with clear Cerebrospinal fluid, allowing optimal visualization with the endoscope. Space-occupying lesions in the ventricular system also frequently cause obstruction of CSF outflow, consequently leading to enlargement of the ventricular system and thus to a larger and more favorable working environment for the surgeon [^1]. In particular, the Lateral ventricle and the Third ventricle are optimally accessible endoscopically for surgical procedures.
For the following conditions, a purely endoscopic or endoscope-assisted operation may be appropriate:
Brain tumors
Brain tumors are generally treated with microsurgery. Exceptions include intraventricular or paraventricular tumors. These do not always require surgical removal, and some tumor types respond well to other forms of treatment. However, histological confirmation of the diagnosis is generally necessary to determine further treatment. If the tumor is located in a site that is favorably accessible endoscopically, an endoscopic biopsy is possible. Compared with conventional biopsy, the endoscopic approach offers a significant advantage through direct visualization of the tumor, as the exact biopsy site can be viewed, resulting in a higher diagnostic yield. Direct hemostasis can likewise be achieved in cases of minor bleeding caused by the biopsy.
Because tumors in the ventricular system can obstruct CSF outflow, the neuroendoscopic approach in such cases allows direct performance of an endoscopic third ventriculostomy or a Septostomy.
In some cases, complete endoscopic removal of an intraventricular tumor is also possible. Tumors that are moderately vascularized and have a soft consistency and a size of < 2-3 cm are particularly suitable for this approach [^7]. If the tumor is adherent to structures such as the Fornix or the Thalamostriate vein, complete resection is often not possible in order to avoid injury to these structures [^8]. The main disadvantage of endoscopic tumor surgery for the surgeon is the restricted maneuverability through the endoscope and the lack of bimanual working capability available in open surgery.
Skull base surgery
Endoscopes enable the surgeon to obtain excellent illumination of the surgical field and correspondingly high-quality images of the operative site, even through a long and narrow access route. Endoscopes also provide, through angled optics, a view of areas of the surgical field that cannot be visualized by direct observation through the operating microscope. Thus, in addition to the classic transcranial approach, the endoscopic approach can be used to perform endoscopically controlled transnasal surgery at the Skull base.
Obstructive hydrocephalus
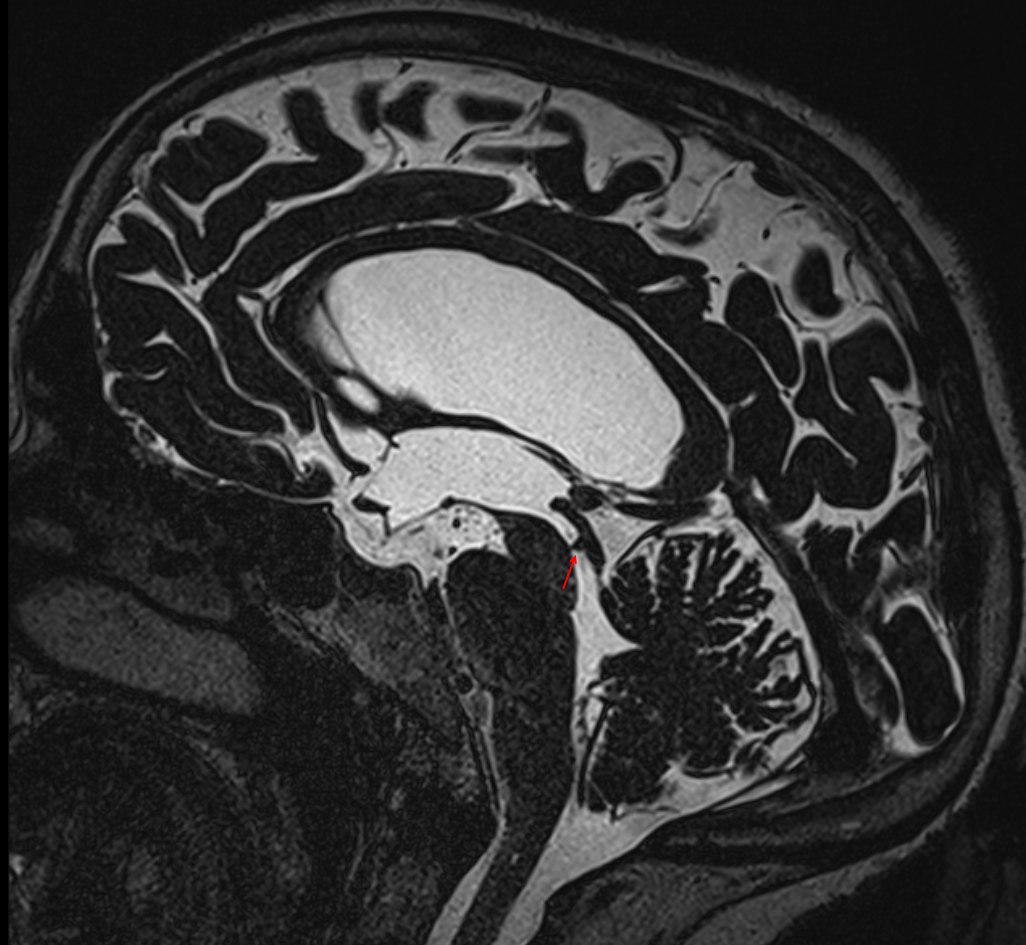
Treatment of Hydrocephalus most commonly consists of creating an artificial CSF diversion through a ventriculoperitoneal shunt (VP shunt). Certain forms of hydrocephalus allow restoration of CSF circulation through a fully endoscopic procedure as an alternative, thereby avoiding implantation of a drainage system. This may be considered, for example, in obstructive hydrocephalus, which may be caused by aqueductal stenosis, cysts, or tumors. An elegant solution in such cases is endoscopic third ventriculostomy (ETV), in which the floor of the third ventricle is opened endoscopically, thereby enabling CSF outflow into the external CSF spaces.
A much rarer form of hydrocephalus may consist of isolated dilation of the temporal horns of the lateral ventricle, which can occur, for example, secondarily as a complication after tumor surgery. There is no standard treatment for this rare condition; however, an endoscopic approach may represent a treatment option in selected cases [^3].
Colloid cysts
Colloid cysts are benign cystic structures lined by an epithelial layer and containing mucoid fluid. Colloid cysts are frequently located in the third ventricle and, depending on their location and size, may obstruct CSF outflow pathways. Asymptomatic or size-stable colloid cysts usually do not require surgical intervention. However, if symptoms caused by the colloid cyst develop, surgical removal is generally indicated [^6]. If surgical cyst resection is necessary, depending on its location and size within the ventricular system, it may be performed microsurgically or, in favorable cases, purely endoscopically.

Arachnoid cyst
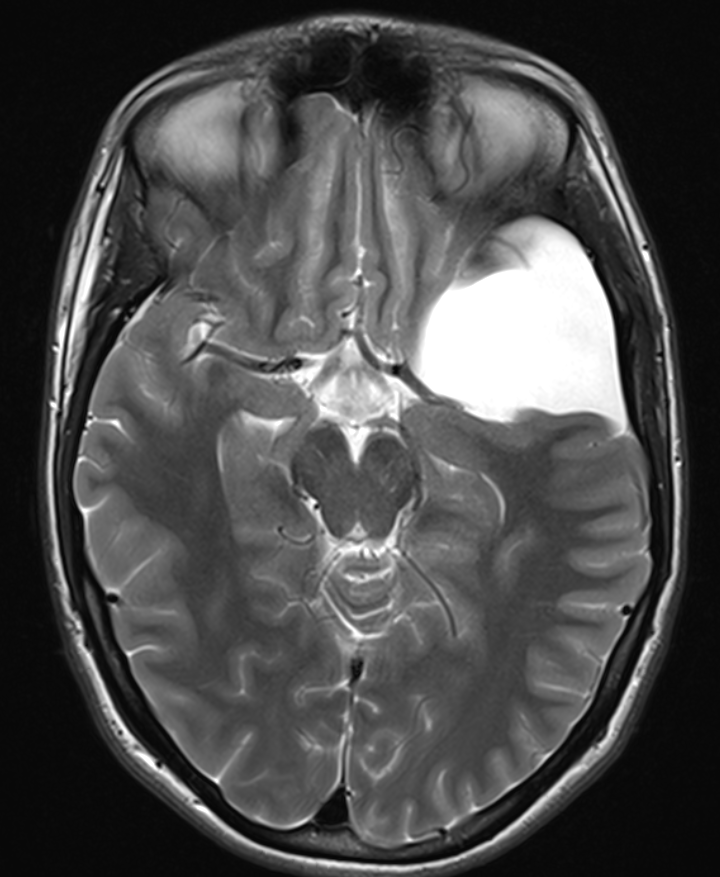
Arachnoid cysts are benign cystic lesions of the Arachnoid mater and are usually asymptomatic, requiring surgical treatment only rarely. Symptomatic cysts or those that increase in size over time may require cyst fenestration. Depending on the location and radiological findings, purely endoscopic minimally invasive cyst fenestration can be performed. Suprasellar arachnoid cysts are particularly suitable because they are frequently accompanied by hydrocephalus. The resulting ventricular enlargement provides good access and allows creation of a large fenestration in the cyst, significantly reducing the likelihood of recurrence. Study data have shown that refenestration is necessary only in the rarest of cases for suprasellar cysts [^4].
However, the neuroendoscopic procedure is not limited to suprasellar arachnoid cysts and can also be used, depending on the available access route, for cysts in the middle and posterior cranial fossa [^5].
Brainstem and cranial nerves
Many delicate structures are located in very close proximity to one another in the region of the brainstem and the cranial nerves. During surgery in this region, the endoscope allows visualization behind these structures without manipulation, helping to understand the individual anatomic relationships and identify the causes of dysfunction. This includes, for example, a pulsating vascular loop as the cause of trigeminal neuralgia or a hemifacial spasm. With the aid of the endoscope, the neurovascular conflict can be precisely localized and the decompression visualized, as endoscopy allows the anatomic relationships at the cerebellopontine angle to be precisely displayed from multiple angles [^9].