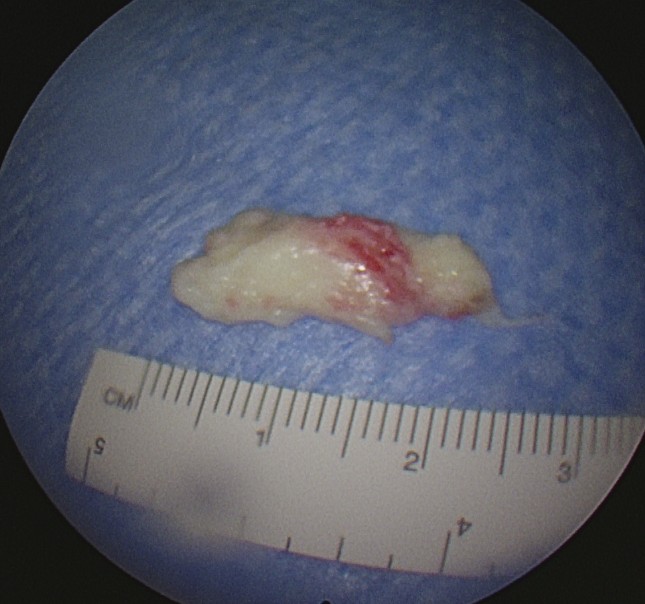
A herniated disc is the displacement of Intervertebral disc tissue beyond the physiological boundaries of the intervertebral space. This can result in mechanical compression and inflammatory irritation of Nerve roots, the Spinal cord, or the Cauda equina. Bulging, characterized by a broad-based protrusion without a circumscribed herniation, must be distinguished from herniation. Morphologically, protrusion, extrusion, and sequestration are differentiated.
Epidemiology
Herniated discs occur predominantly in the lumbar spine. The L4/5 and L5/S1 segments are most commonly affected. Cervical disc herniation occurs preferentially at the C5/6 and C6/7 levels. Thoracic herniations are considerably less common but may be particularly clinically relevant because of the potential for spinal cord compression. The lifetime risk of developing a lumbar disc herniation is approximately 1-3%, with 60-90% of these herniated discs improving spontaneously[^1].
Etiology and pathophysiology
The cause is usually a degenerative change in the annulus fibrosus with loss of fluid from the nucleus pulposus. Axial loading and rotational forces may subsequently lead to displacement of disc tissue. Neurological symptoms arise both from direct compression and from local inflammatory mediators.
Clinical presentation
Symptoms depend on the location and the neural structure affected:
Lumbar: Lumbosciatica, dermatomal sensory disturbance, paresis, and diminished reflexes
Cervical: cervicobrachialgia, sensory or motor radicular deficits, and, in the presence of spinal cord compression, signs of cervical Myelopathy
Thoracic: radicular, frequently band-like pain, gait disturbance, spastic paresis, or autonomic dysfunction
A radiologically confirmed herniated disc is not automatically symptomatic. The clinical-radiological correlation is decisive.
Red flags
Cauda equina syndrome with urinary retention or incontinence, saddle anesthesia, fecal incontinence, or reduced anal sphincter function constitutes a neurosurgical emergency. Rapidly progressive paresis and acute, clinically significant spinal cord compression also require immediate specialist assessment.
Diagnostics
Clinical assessment
The foundation consists of the medical history and a complete neurological examination, including assessment of strength, sensation, reflexes, and pyramidal tract signs. If cauda equina syndrome is suspected, perianal sensation, sphincter tone, and bladder function must also be assessed. The precise neurological assessment depends on the location of the herniated disc.
Imaging
Magnetic resonance imaging is the imaging modality of choice.
